What changes on testosterone, when it happens, how to understand size, and ways to care for a changing body.
Bottom growth can be one of the most noticeable (and least clearly explained) effects of testosterone. Readers often want more than a definition: What will it look like? How much growth is possible? Will clothing feel uncomfortable? What does a measurement in centimeters actually mean?
This guide explains FTM bottom growth using clinical terminology, practical care advice and illustrations. It is written for trans men, transmasculine people and nonbinary people considering or using testosterone. You can use the words that feel right for your own body; anatomical terms here help identify which structures are being discussed.
About this guide
This is general education, not a diagnosis or an individualized treatment plan. Hormone decisions belong in a conversation with a qualified prescribing clinician. The anatomy illustrations are general schematics, not predicted treatment results.
What changes
Testosterone can enlarge clitoral tissue, changing its visible size and the way it feels.
When it develops
Clinical guidance places onset around 1–6 months, with development commonly continuing over 1–2 years.
What varies
Starting anatomy, hormone response, hood coverage and how a measurement is taken all affect comparisons.
On This Page
What Is FTM Bottom Growth?
Bottom growth is a community term for enlargement of the clitoris during testosterone therapy. The visible glans and shaft may become more prominent. This is an effect of hormones on existing tissue; it is different from genital surgery. [1]
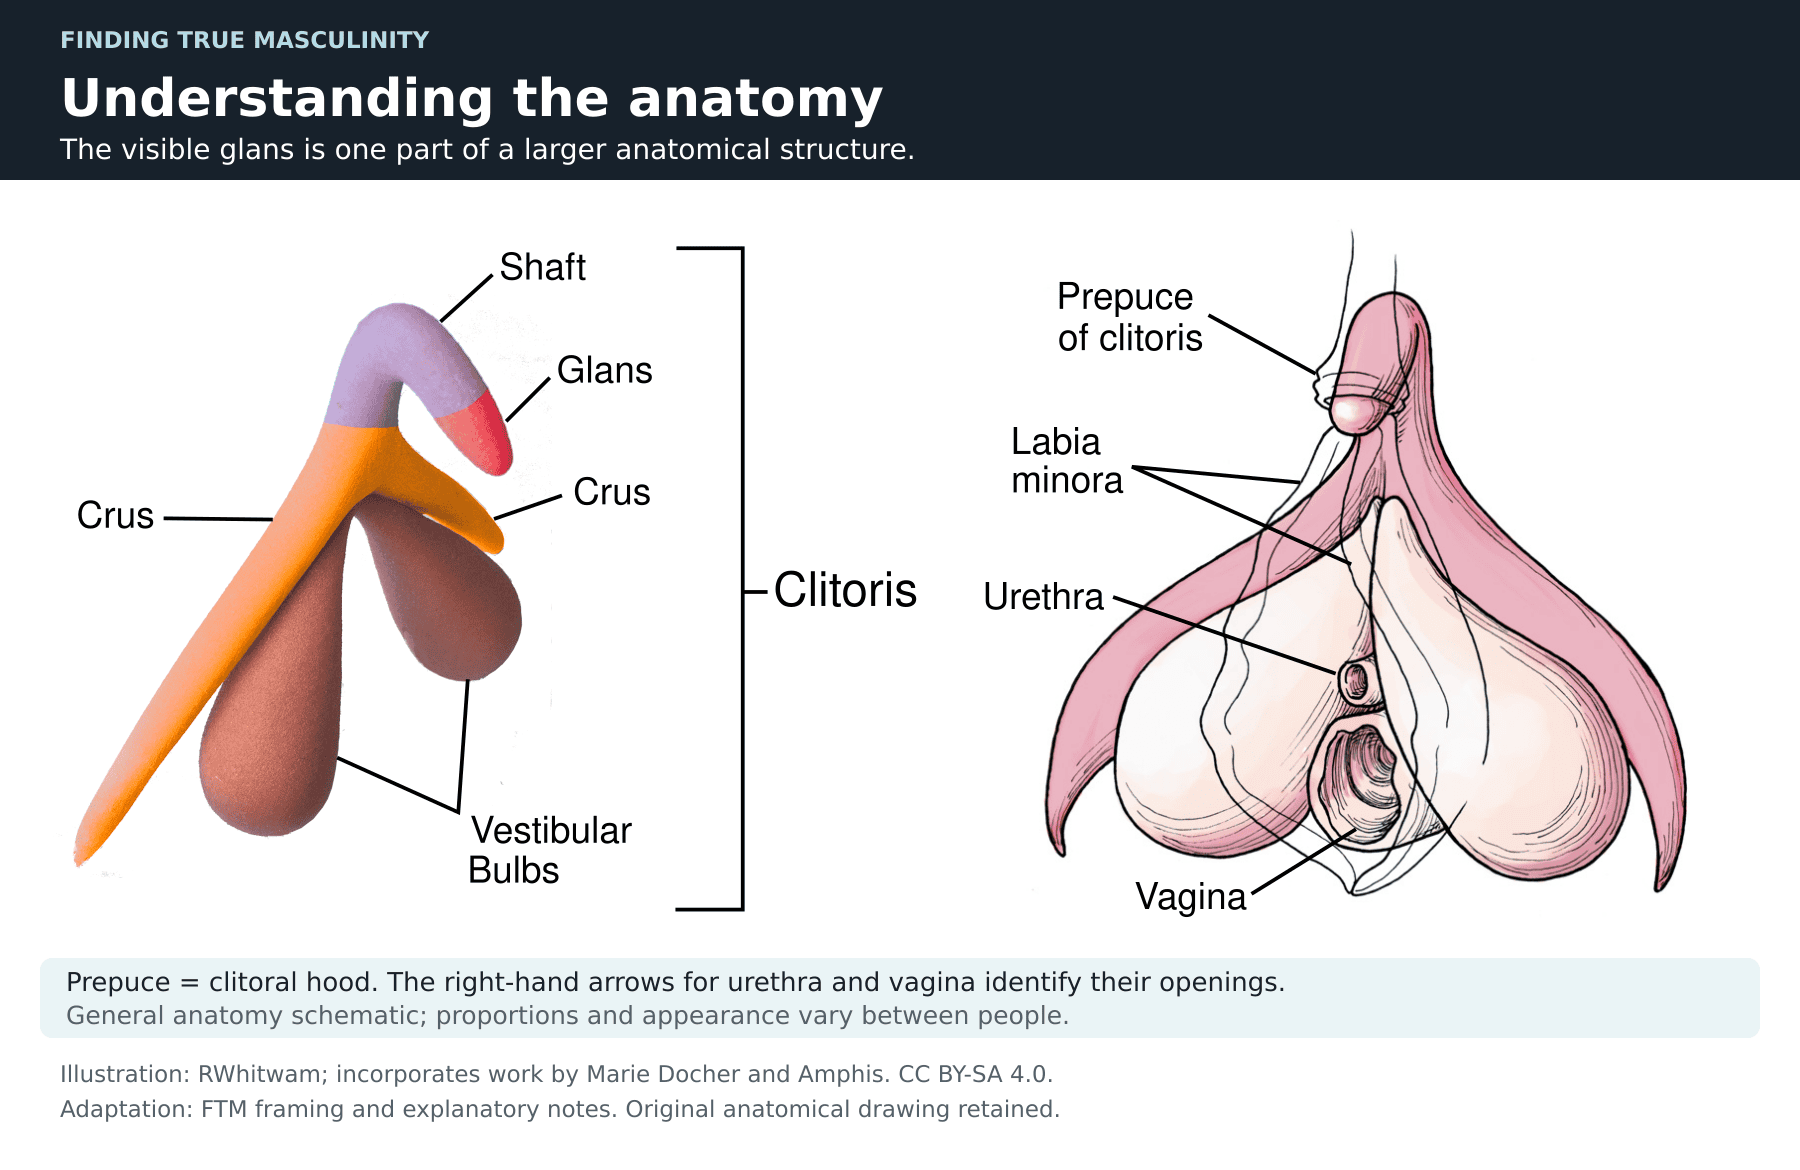
Understanding the anatomy makes this easier to picture. The glans is the visible tip; the body or shaft continues behind it, and the paired crura extend internally. The hood, also called the prepuce, is a fold of tissue covering some or all of the glans. [3]
Bottom growth does not need to be someone’s main reason for starting T. Some people welcome it, some are uncertain, and others would prefer different effects. Learning about it beforehand gives you a clearer basis for discussing your goals.
Bottom Growth Timeline: When Do Changes Happen?
The Endocrine Society’s clinical guideline lists clitoral enlargement as beginning around 1–6 months after starting testosterone, with maximum development generally estimated at 1–2 years. These are clinical estimates, not deadlines or a promise about your individual result. [2]
| Period | What the timing can tell you |
|---|---|
| First weeks to months | Awareness or sensation may change early. A subtle early change is not enough to predict final size. |
| About 1–6 months | The guideline’s estimated onset window. Visible changes may become easier to recognize as treatment continues. |
| About 1–2 years | The guideline’s estimated period for reaching maximum development. Progress does not have to be steady from month to month. |
| Beyond the estimated window | A timeline cannot identify the cause of a new lump, painful swelling or a sudden change. New symptoms need assessment rather than being assumed to be growth. |
It is more useful to discuss your overall response at scheduled follow-ups than to judge treatment by a weekly size check. Bring up changes that concern you, along with your dose history, other effects and any symptoms. Your clinician can interpret those details together.
What Does Bottom Growth Look Like?
There is no single appearance that everyone develops. More tissue may be visible beyond the hood, or much of it may remain covered. Hood coverage, surrounding tissue and viewing angle can make two bodies with a similar measured length look quite different. [3]
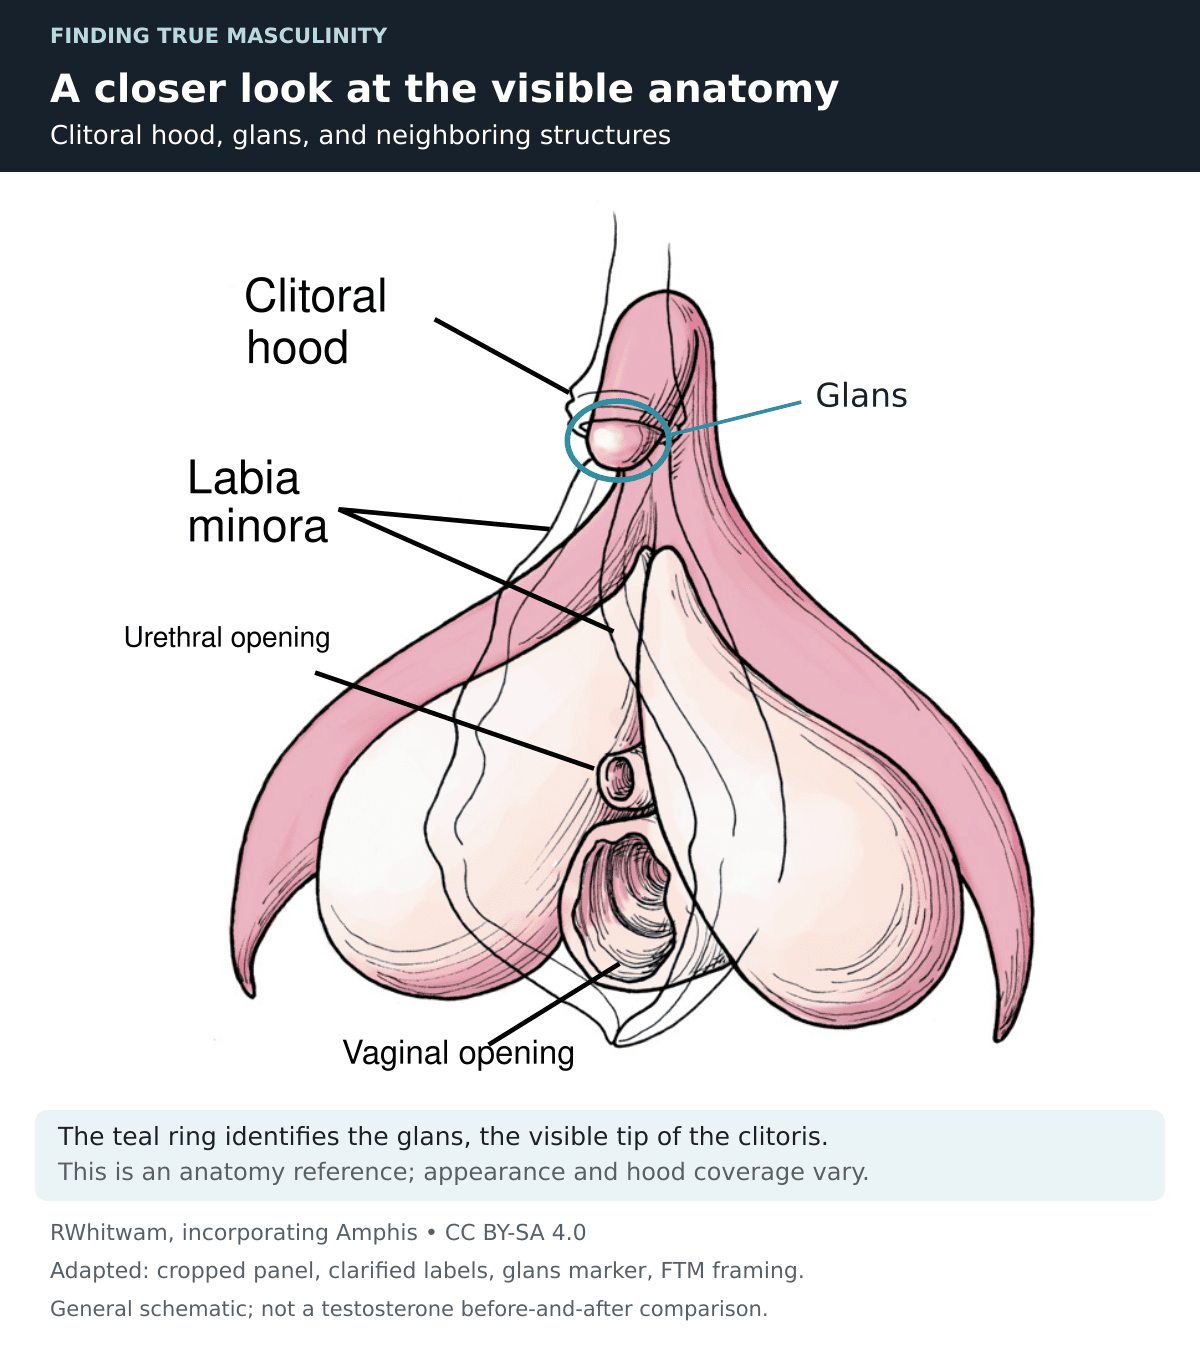
Arousal can also make the tissue look larger or firmer. That temporary change should be distinguished from the longer-term enlargement associated with testosterone. Comparing an aroused photo with an unaroused one can make the apparent change misleading. [1]
Use the illustrations as a map
Their job is to identify structures. They are not templates for how your body should look, and neither diagram shows a specific stage of testosterone treatment.
How Big Can Bottom Growth Get?
The most important distinction is additional growth versus final length. An increase of 2 cm means 2 cm beyond a starting measurement. A final length of 2 cm means the whole measured length is 2 cm. Those statements are not interchangeable.
For context, a 2021 review of androgen-related development describes up to about 2 cm of additional growth in transmasculine patients. An older longitudinal study reported a mean maximal clitoral length of 4.6 cm by one year of therapy. These describe different quantities and research settings; neither is a universal target or a guaranteed result. [4] [11]
The older study is useful for illustrating why wording matters, but it should not be presented as a current population-wide average. A study’s group mean also cannot tell you what any one person will experience.
Before trusting a size claim, ask: Is it final length or added length? Is the tissue resting, aroused or stretched? Is the writer measuring only what is externally visible? Was the sample drawn from people seeking surgery? A 2023 metoidioplasty study, for example, specifically discusses stretched clitoral length—a different measure from a casual visible-length comparison. [12]
A range is not a score
Having less visible growth than someone else does not make a transition less valid. A size measurement alone does not determine comfort, satisfaction or whether treatment is meeting your goals.
What Do These Measurements Look Like?
Centimeters can be difficult to picture. The graphic below places exact 1–5 cm bars beside familiar objects and gives each object’s actual dimension. The examples explain units; 1–5 cm is not being presented as a normal range or an expected progression.
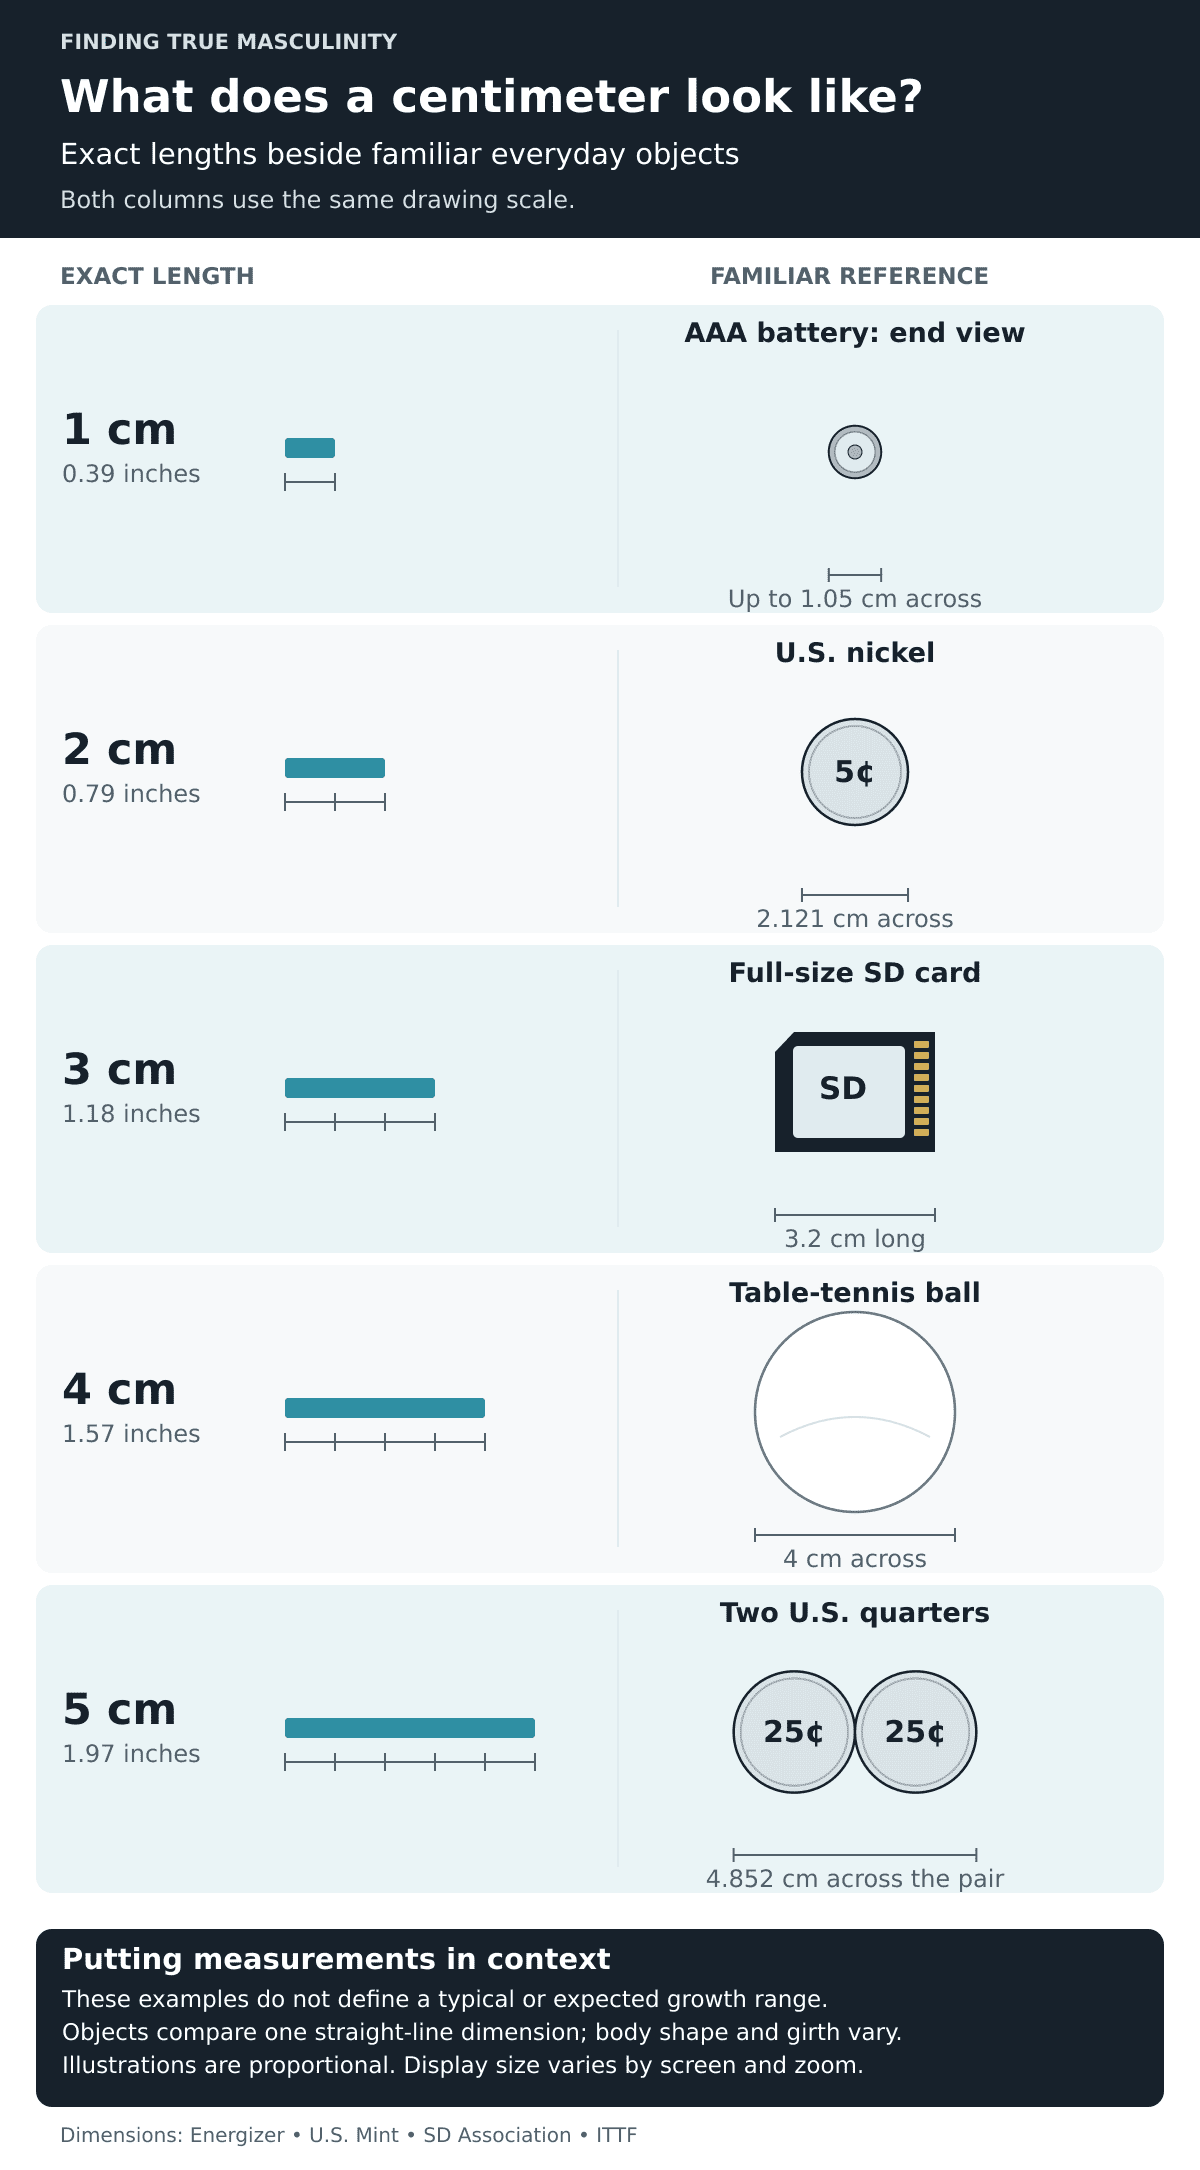
Notice that the comparisons are approximate: a nickel is 2.121 cm across, not exactly 2 cm, and a full-size SD card is 3.2 cm along its longer edge. A table-tennis ball illustrates a 4 cm line across its diameter; its round shape is not a comparison to the shape or thickness of genital tissue.
For quick conversion, 1 inch equals 2.54 cm. That makes 2 cm about 0.79 inches, 3 cm about 1.18 inches, and 4 cm about 1.57 inches. The labeled dimensions are more useful than trying to hold a ruler against your screen.
Understanding and Tracking Measurements
You do not have to measure your body to monitor a transition. If keeping a record helps you, consistency matters more than finding the most flattering number. A change in technique can create an apparent gain or loss that is not a lasting physical change.
- Write down what you are measuring: visible length, a clinician’s measurement, or change from your own starting point.
- Keep the conditions comparable. Do not compare a resting measurement with one taken during arousal.
- Use a clean ruler gently alongside the tissue. Do not press into tender tissue or force the hood back.
- For personal tracking, avoid stretching or pulling to reproduce a measurement described in a surgical study. Ask a clinician to explain that method if it is relevant to your care.
- Space out records if repeated checking becomes uncomfortable or fuels anxiety. Photos and measurements are optional, private information.
A consistent record may help you explain a concern, but it is not a diagnostic test. If something has become painful, swollen or different suddenly, seek care instead of trying to settle the issue with more measurements.
Sensitivity, Clothing and Everyday Comfort
More prominent or exposed tissue can be more noticeable against clothing or during touch. Sensitivity is individual: a sensation that feels affirming to one person may feel distracting or unpleasant to another. Strong or persistent pain should not be treated as proof that growth is happening. [3]
Practical ways to reduce friction
- Try soft underwear with seams positioned away from sensitive tissue.
- Choose roomier pants or underwear when pressure is uncomfortable.
- Change out of damp clothing and avoid repeatedly rubbing or checking a tender area.
- If packing, reassess the packer’s position and how the pouch or harness presses against your body.
- Pause an activity or product that repeatedly causes soreness; comfort is useful feedback.
Packing gear that felt fine before may sit differently against newly sensitive tissue. Our binding and packing guide covers positioning, securing options and care. You can adjust a setup without treating discomfort as something to push through.
Cleaning and Daily Care
Keep care gentle. NHS vulval-care guidance recommends washing with water or a suitable soap substitute, avoiding irritating products and drying without rubbing. More aggressive cleaning is not necessarily better for sensitive skin. [5]
- Wash the external area gently, using comfortable warm water. If a clinician recommends a cleanser or emollient for a skin condition, follow that advice.
- Clean accessible folds gently. Move the hood only as far as it comfortably allows; do not force it.
- Avoid perfumed washes, deodorants, scrubs and harsh antiseptics on sensitive genital tissue.
- Pat dry rather than rubbing. Avoid repeatedly washing a sore area in an effort to make it feel cleaner.
- Seek advice for persistent buildup, painful hood movement, sores or ongoing irritation instead of scraping or picking at the tissue.
External care is separate from internal vaginal cleaning. Do not douche. If odor, discharge or irritation changes and persists, cleaning harder is not a substitute for finding the cause. [5]
Sexual Function, Arousal and Sensation
Testosterone can change libido, arousal and orgasm sensations. Some people find familiar touch feels different or that their preferences shift. Arousal-related enlargement is temporary; it does not measure permanent growth. [1]
If you choose to explore touch, start gently and adjust pressure, contact and lubrication for comfort. Tell a partner what feels good and what does not. There is no requirement to enjoy direct contact with the glans, and no requirement to be sexually active to feel at home in your body.
Dryness or pain with penetration can be a separate issue from external sensitivity. Testosterone-related changes in vaginal tissue, infection and pelvic-floor problems can all contribute to discomfort. A clinician can assess the cause and discuss options, including moisturizers, lubricants, pelvic-floor care or local treatment when appropriate. [6]
Testosterone is not contraception. If your anatomy and sexual activity make pregnancy possible, use appropriate birth control even if periods have stopped. A clinician can help you choose an option that fits your goals. [13]
Sensation is not a performance test
A larger visible size does not establish what activities will be comfortable or satisfying. Use your own comfort and preferences to guide exploration; persistent pain deserves care.
Is Bottom Growth Permanent?
Clitoral growth is generally considered a permanent effect of testosterone. Mayo Clinic includes it among changes that do not reverse after treatment stops. Stopping T should not be approached as a reliable way to return the tissue to its previous size. [13]
This matters if you are considering a short course or a lower dose because you want only certain effects. Bring a concrete list of wanted, unwanted and uncertain changes to a prescribing appointment. Slower changes do not mean you can select every individual effect or undo one later.
For a broader view of the changes that may accompany T, see 12 effects to expect on testosterone. The decision is about the overall balance of effects and your goals, not just one measurement.
Can You Increase Bottom Growth? What Claims Need Caution
Searches about bottom growth often lead to promises of faster or larger results. Before spending money or changing treatment, separate evidence about systemic testosterone from claims about an add-on product.
Higher testosterone doses
UCSF’s prescribing guidance states that, once levels are in the normal male physiological range, there is no evidence that higher testosterone levels produce greater masculinization. That is different from adjusting an insufficient regimen under clinical supervision. More medication is not a reliable shortcut to more growth. [7]
DHT and topical hormone products
Dihydrotestosterone (DHT) is an androgen involved in genital development, but research in one population or age group cannot simply be turned into a home treatment plan for another. The 2021 review emphasizes gaps in evidence about which additional hormonal approaches, if any, are best for adult transmasculine growth. It does not establish a universal topical regimen. [4]
Do not apply your usual testosterone gel to genital tissue to target growth. Use it only on the sites specified for that product and your prescription. Genital application is not the same as taking a prescribed systemic dose. [7]
Pumps, supplements and enlargement claims
A temporary increase in swelling is not evidence of permanent tissue growth. Mayo Clinic describes vacuum-pump enlargement of the penis as temporary and notes risks from excessive use. That guidance concerns penile devices; it does not establish effectiveness or a safe regimen for clitoral enlargement. [8]
Treat permanent-growth claims for pumps, creams or supplements cautiously. Ask for research on the specific product, the population studied, how results were measured and how long they lasted. Stop a device that causes pain, bruising, numbness or skin injury and seek medical advice.
Bottom growth and metoidioplasty
Metoidioplasty uses testosterone-enlarged clitoral tissue to construct a small phallus. It is surgery, with its own assessment, techniques and tradeoffs. A ruler measurement or comparison photo cannot determine whether someone is a candidate or predict their surgical outcome. [9]
Expectations, Euphoria and Mixed Feelings
It is possible to feel excited about bottom growth and still need time to adjust. It is also possible to want facial hair or a deeper voice while feeling uncertain about genital changes. Neither reaction needs to be turned into a test of gender identity.
Comparisons can become especially unhelpful when they mix aroused photos, surgical results and ordinary hormone-related changes without explanation. A useful guide should help you understand those differences, not give you another standard to measure yourself against.
If the change feels distressing, identify the specific concern: sensation, appearance, permanence, hygiene, intimacy or something else. A focused question is easier to address than a general fear that your body is developing incorrectly. A gender-affirming clinician or therapist can help you explore those concerns without assuming which outcome you should want.
When to Seek Medical Care
Not every new genital symptom is bottom growth. Persistent pain can have several causes, including irritation, infection, tissue changes and pelvic-floor problems. Getting the cause assessed is more useful than assuming it is an unavoidable part of taking T. [6]
Arrange a medical appointment for:
- Pain or burning that persists, worsens or repeatedly returns.
- Sores, broken skin, a new lump or an area that stays swollen.
- Painful movement of the hood or persistent difficulty cleaning comfortably.
- New or unusual discharge, ongoing itching or urinary symptoms.
- Pain with arousal, orgasm or penetration that is affecting your life.
When to get urgent help
Seek urgent medical advice for pelvic pain with fever, difficulty passing urine, unusual bleeding or possible pregnancy. Severe or worsening pelvic pain, fainting or heavy bleeding needs emergency assessment. Use the urgent-care or emergency service where you live. [10]
You can tell a clinician which anatomical words you prefer, ask them to explain an examination before it begins and request a pause. You do not need to tolerate unexplained pain to prove you can handle transition.
Frequently Asked Questions
Can bottom growth happen on a low dose of testosterone?
Yes. A lower dose does not reliably exclude this effect. Discuss unwanted permanent changes before treatment rather than relying on dose alone to prevent them. [1]
Can testosterone gel cause bottom growth?
Yes. Gel is a way to deliver systemic testosterone. A gel regimen is not a guarantee of smaller genital changes. Use the prescribed application sites; applying it directly to genital tissue is not a growth strategy. [7]
Is 2 cm of growth the same as a final length of 2 cm?
No. Added growth is the difference from a starting measurement. Final length includes the starting length. A comparison is incomplete unless it explains which quantity and measurement method it uses.
Does more soreness mean more growth?
Pain intensity cannot tell you how much permanent growth is occurring. Do not use soreness as a progress marker. Persistent or worsening pain should be assessed.
Can you prevent bottom growth while getting every other effect of T?
There is no dependable way to select every effect individually. Discuss your priorities and concerns with your prescriber. Do not add hormone-blocking medicines yourself in an attempt to isolate particular changes. [1]
Will bottom growth disappear if I stop testosterone?
It is generally considered permanent. Do not assume that stopping testosterone will restore the previous size. [1]
Will I need surgery because I have bottom growth?
No. Hormone-related growth and decisions about genital surgery are separate. Some people later explore metoidioplasty or phalloplasty; others do not want surgery.
Does the size graphic show how large I should become?
No. It explains centimeters using familiar objects. The 1–5 cm bars are reference lengths, not a growth schedule, target, normal range or prediction.
Practical Takeaways
Bottom growth is easier to understand when anatomy, timing, measurement and comfort are discussed separately. Give yourself room for an individual response, question claims that promise a particular size, and bring persistent symptoms to a clinician. Your body does not have to match an illustration or someone else’s timeline.
Sources and Further Reading
Sources were checked for this update. Clinical estimates, historical studies, general skin-care guidance and surgical cohorts answer different questions; they should not be combined into a single guaranteed growth range.
- UCSF Gender Affirming Health Program — Information on Testosterone Hormone Therapy — Patient information on hormone effects, sexual changes and permanence.
- Hembree et al. — Endocrine Society clinical practice guideline (2017), Table 12 — Clinical estimates for onset and maximum development; these are not individualized predictions.
- Cleveland Clinic — Clitoris: Anatomy, Location, Purpose & Conditions — Anatomical terminology, hood variation and sensitivity.
- Grimstad et al. — The role of androgens in clitorophallus development and possible applications to transgender patients (2021) — Review distinguishing additional growth and gaps in evidence for hormonal approaches. DOI: 10.1111/andr.13016.
- Kent Community Health NHS Foundation Trust — Vulva care — Gentle external skin care and avoiding irritants.
- UCSF — Pelvic pain and persistent menses in transgender men — Differential causes of pain, vaginal tissue changes and individualized care.
- UCSF — Overview of masculinizing hormone therapy — Dosing, monitoring and appropriate gel application.
- Mayo Clinic — Penis-enlargement products: Do they work? — Context for temporary pump effects and enlargement claims; not a study of clitoral pumping.
- Mayo Clinic — Masculinizing surgery — Overview of metoidioplasty and other surgical options.
- NHS — Pelvic pain — Symptoms requiring urgent or emergency assessment.
- Physical and hormonal evaluation of transsexual patients: a longitudinal study (1986) — Historical study reporting mean maximal clitoral length. Its result is not a modern population-wide target; the original title uses older terminology.
- Assessment of neophallus length following metoidioplasty (2023) — A surgical cohort illustrating the distinction between stretched tissue measurements and exposed length.
- Mayo Clinic — Masculinizing hormone therapy — Permanence of physical changes and pregnancy/contraception considerations.
Dimensions used in the comparison graphic
- Energizer E92 specification — AAA maximum diameter: 10.5 mm.
- U.S. Mint coin specifications — nickel: 21.21 mm; quarter: 24.26 mm across.
- SD Association form factors — full-size SD card: 32 × 24 mm.
- International Table Tennis Federation — regulation ball diameter: 40 mm.
Illustration source and license
The anatomy images are adapted from “Anatomy of clitoris and associated structures” by RWhitwam, incorporating earlier work by Marie Docher and Amphis. The source and adapted anatomy images use Creative Commons Attribution-ShareAlike 4.0. Specific changes are identified in each caption. The diagrams are educational schematics, not independently clinician-reviewed illustrations of testosterone outcomes.